


Who Pays for Medical Evacuation?
Who pays for medical evacuation? Learn when insurance, travel coverage, employers, or families cover air ambulance costs and what to verify fast.
A medical evacuation often gets arranged when time is short, the patient is unstable, and the current facility cannot provide the level of care required. In that moment, one of the first questions families, case managers, and insurers ask is who pays for medical evacuation. The answer depends on the medical necessity of the transport, where the patient is located, what type of policy is in force, and whether the move is an emergency evacuation, an interfacility transfer, or a repatriation.
Who pays for medical evacuation in most cases?
There is no single payer in every case. Payment may come from a private health insurance plan, a travel insurance policy, an employer-sponsored international policy, workers' compensation, government coverage in limited situations, or the patient and family directly. In some transports, more than one party is involved. A health plan may cover the medically necessary portion, while the patient remains responsible for noncovered charges, cross-border administrative costs, or upgraded transport arrangements.
This is why coverage verification matters early. The phrase "air ambulance" may appear in a policy, but the actual benefit can be narrow. Some plans cover emergency transport to the nearest appropriate facility but do not cover transfer back home. Others cover domestic flights but not international medical repatriation. The details change the financial outcome.
The biggest factor is medical necessity
For most insurers, payment starts with medical necessity. That generally means the patient cannot safely travel by commercial airline, private vehicle, or ground ambulance, and the sending facility cannot provide the level of care required. The receiving hospital must usually be appropriate for the patient's condition, not simply more convenient.
If a physician documents that the patient needs ICU-level monitoring, ventilator support, neonatal transport, ECMO capability, high-risk obstetric management, or another advanced critical care service during flight, coverage is more likely to be considered under medical transport benefits. If the transfer is mainly for personal preference, family proximity, or comfort, coverage becomes less likely.
That distinction matters in international cases. A traveler injured abroad may be stable enough for treatment locally but still want to return to the United States. From the family's perspective, that is understandable. From the insurer's perspective, it may be classified as elective repatriation rather than emergency evacuation.

Private health insurance may pay - but not automatically
Private health insurance can pay for medical evacuation, especially when the transport is urgent and clinically justified. That said, approval is rarely automatic. The insurer may require preauthorization unless the situation is an immediate emergency. It may also limit the approved route, aircraft type, clinical crew level, or destination hospital.
In domestic cases, a commercial health plan may cover an air ambulance from one hospital to another if the patient needs specialized care unavailable locally. In international cases, standard health insurance often becomes more restrictive. Some plans offer little or no international transport benefit, even if they cover emergency medical treatment abroad.
Out-of-network issues also affect payment. If the air ambulance provider is not contracted with the plan, the insurer may approve only part of the charges or reimburse based on its own schedule. The remaining balance may fall to the patient, depending on the plan terms and applicable regulations.
Travel insurance is often the clearest fit for travelers abroad
If the patient became ill or injured while traveling, travel insurance may be the most relevant coverage. Many travel policies include emergency medical evacuation benefits specifically for transport to the nearest adequate medical facility or, in some policies, to the home country when medically appropriate.
This is where policy language matters. Some plans are designed for vacation travel and include evacuation only for acute emergencies. Others include political evacuation, security extraction, or broader repatriation services. High-limit plans may cover substantial air ambulance costs, while lower-cost policies may have caps that do not fully meet the cost of a long-range critical care flight.
Travel assistance membership programs can also be part of the picture, but they are not the same as insurance. Some arrange transport under specific conditions, while others mainly coordinate logistics. Families should confirm whether the program is promising direct payment, reimbursement, or only assistance.
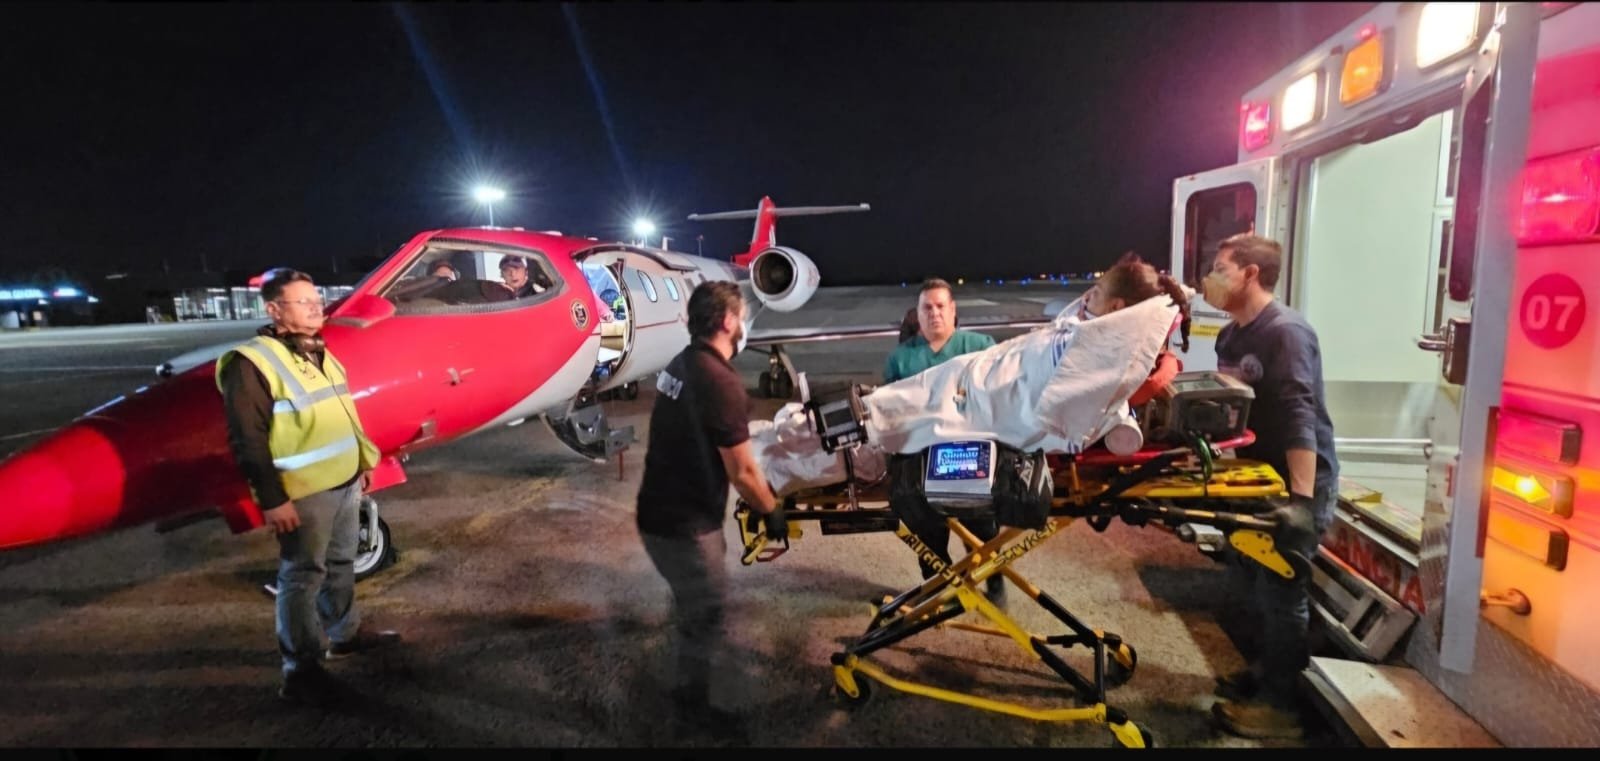
Employers, government entities, and workers' compensation
For executives abroad, offshore workers, humanitarian teams, and government personnel, the payer may be an employer or agency-backed insurance plan. These policies are often built for international assignments and may include evacuation and repatriation benefits that standard domestic health insurance does not.
Workers' compensation may pay when the injury or illness is work-related and the transport is necessary because of the job incident. This is common in industrial, maritime, energy, aviation, and remote-site environments. The same principle can apply to corporate risk management programs, where the employer has contracted for emergency evacuation services in advance.
Government coverage varies. Medicare generally does not function like a broad international evacuation plan, and patients should not assume that a federal health benefit will pay for overseas air ambulance transport. Medicaid rules are even more limited and state-specific. In military or diplomatic contexts, separate systems may apply.
When the family pays out of pocket
In many real-world cases, the family or patient pays some or all of the cost. This happens when there is no applicable insurance, when the transport is denied as not medically necessary, when the destination is based on preference rather than clinical need, or when international repatriation falls outside the benefit structure.
Out-of-pocket payment is also common when speed is the deciding factor. In urgent cross-border cases, families may choose to proceed immediately while benefit verification is still underway. A qualified transport coordinator can often help obtain documentation for reimbursement later, but reimbursement is never guaranteed.
That is why financial clarity should be part of the transport planning process, not an afterthought. A serious provider should be able to explain what is included in the quote, what clinical crew and equipment are required, and what records are needed for insurance review.
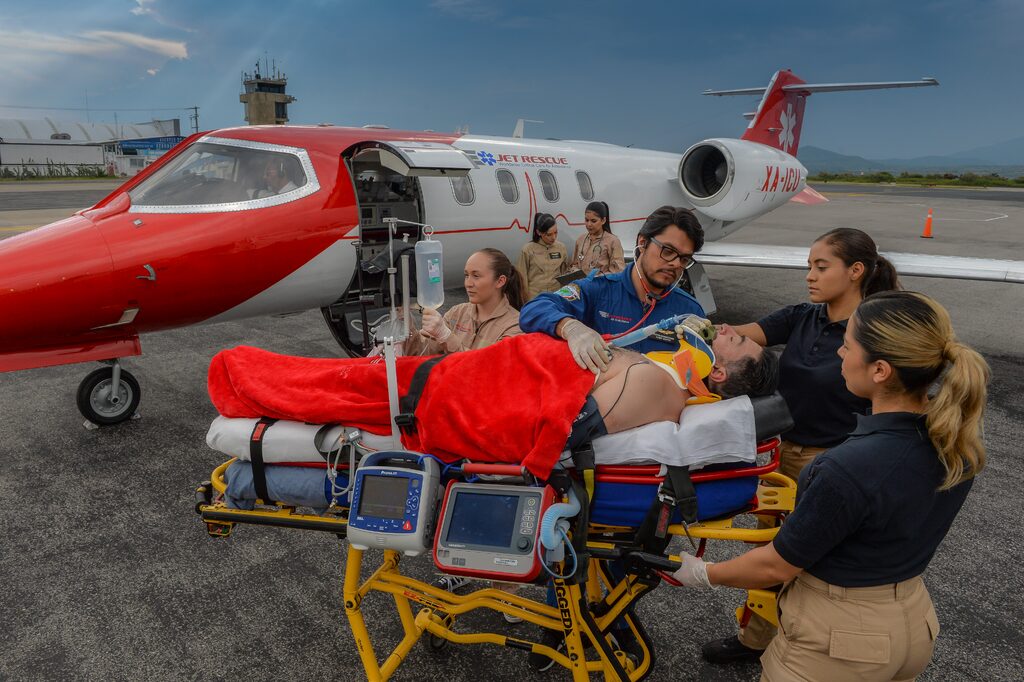
What insurers usually want before they approve payment
If you are trying to determine who pays for medical evacuation, expect the insurer or assistance company to ask for the patient's diagnosis, current condition, treating physician notes, hospital records, and the reason a lower-acuity mode of transport is unsafe. They may also ask why the current hospital cannot continue care and why the receiving facility is clinically appropriate.
For international cases, they often want passport details, location information, admitting hospital contacts, and confirmation that the receiving hospital has accepted the patient. Delays frequently occur when medical records are incomplete or when the sending and receiving physicians have not aligned on the transport plan.
A specialized operator can help move this process faster by coordinating directly with hospitals, bedside teams, case managers, and insurance representatives. In high-acuity cases, that operational support is not a convenience. It can determine whether the transfer happens on time.
Common coverage gaps families do not expect
The most common misunderstanding is assuming that if emergency care is covered, evacuation is covered too. That is not always true. Another problem is assuming the policy covers return to the patient's hometown hospital. Many plans cover only transport to the nearest facility that can provide appropriate treatment.
International bedside-to-bedside transport can also involve costs outside the flight itself. Ground ambulances, airport handling, permits, multilingual coordination, customs issues, and escort needs may not all be covered in the same way. Neonatal, pediatric, obstetric, and ECMO transports can require highly specialized teams and equipment, which may affect both approval and cost.
What to verify before the flight is arranged
Before authorizing a transport, confirm who is financially responsible if insurance approves only part of the case. Ask whether the quote includes medical crew, equipment, ground transfers, and international coordination. Confirm whether preauthorization is required, whether reimbursement is possible after transport, and whether the destination has already been accepted by the receiving physician and hospital.
If the case is urgent, ask the provider to work directly with the payer while preparing the aircraft and clinical team. Experienced operators such as Jet Rescue Air understand that benefit verification and mission readiness often need to happen at the same time, especially in cross-border and high-acuity transfers.
When a patient needs to move quickly, the right question is not just who pays for medical evacuation. It is who can verify coverage, document medical necessity, and launch a safe transport without losing critical time.
The order to make the calls in
Who pays is settled faster when the calls are made in the right sequence. Out of order, each party waits on another and days are lost while the patient stays where they are.
First, the health plan, to establish whether air ambulance is a covered benefit and whether prior authorization is required. Second, any travel insurance or assistance membership, which often responds where a domestic health plan will not and frequently has a notification deadline that voids the benefit if missed. Third, the employer, if the illness or injury is work-related or the patient was travelling on company business, because corporate policies and workers' compensation sometimes cover what personal plans exclude. Fourth, the consulate, which does not pay but can help with documents and with locating family. Only then does the question of self-payment arise.
When nobody is going to pay
A large share of medical evacuations are paid for privately, either because there is no coverage or because the plan will not cover the route. This is not an unusual situation and it does not have to be an open-ended one.
Ask for a fixed, all-inclusive price agreed in writing before you commit: aircraft, flight crew, medical crew, equipment, ground ambulance at both ends, landing, handling and permits, as one number. The alternative, a per-hour quote with items billed afterwards, is how a figure that sounded manageable becomes one that is not. A reputable operator will quote the whole mission and stand behind it.
Ask also whether the patient genuinely needs a dedicated aircraft. For a stable patient, a medical escort on a commercial airline, or an airline stretcher, is often clinically adequate and costs a fraction of a dedicated jet. An operator willing to tell you that is giving up the larger sale, which is precisely why the advice is worth something.
When the hospital is the one arranging it
A separate situation arises when the patient is a foreign national in a United States hospital with no funding source, medically stable, and with nowhere to be discharged to. Here the payer question is usually answered by the hospital itself, because repatriation is the only discharge pathway available and the alternative is an uncompensated stay that continues indefinitely.
These cases turn on the receiving side rather than the aircraft. A hospital in the home country has to have a bed, a service willing to take the case, and in many countries a formal acceptance through the regional health authority. Where the patient has no passport, an emergency travel document has to be issued by the consulate. Where relatives need to be located or civil records obtained, that work runs in parallel rather than afterwards.
Any transport arranged this way should rest on documented consent from the patient or a properly authorised surrogate, a named receiving facility that has accepted in writing, and a fitness-to-fly assessment from the treating physician. Those three things are what separate a legitimate repatriation from the cases that have drawn criticism and litigation.
What to have ready before the first call
Whoever ends up paying, the same information moves the case forward: the insurance card front and back if there is one, the patient's name and date of birth, the hospital and treating physician, a current medical summary, and the destination city or receiving facility. If there is no passport, say so at the outset rather than discovering it later, because the travel document is often the longest item on the critical path.
Tell us about the patient
A mission coordinator answers 24 hours a day. The benefits review is free and carries no obligation.