


Who Needs Medevac? When Air Transport Is Needed
Who needs medevac? Learn when a medical flight, helicopter, or escorted commercial transfer is the safest option for urgent patient care and repatriation.
A patient does not need to be in cardiac arrest to need an air ambulance. The real question behind who needs medevac is whether the patient can reach the required level of care safely, within the available time, by ground or commercial travel. When the answer is no, medically supervised air transport may be the right clinical and logistical solution.
Medevac is not a single service or a diagnosis. It is a coordinated medical transport decision involving the treating physician, receiving facility, transport medical team, and often the patient’s family, insurer, or case manager. The appropriate aircraft, crew, equipment, and route depend on the patient’s condition and the urgency of the transfer.
Who needs medevac?
Patients need medevac when their medical needs exceed what ordinary transportation can safely provide or when distance creates an unacceptable delay in treatment. A medical flight can move a patient between hospitals, return an injured traveler home, or bring specialized clinical support to a remote location.
The need is usually driven by a combination of medical acuity, time, distance, and destination. A stable patient may still require an air ambulance if they need to travel internationally with oxygen, monitoring, medication management, or a medical escort. Conversely, a critically ill patient may require a fully equipped critical care jet even for a relatively short transfer if ground transport would be too slow or clinically limiting.
Critically ill patients needing higher-level care
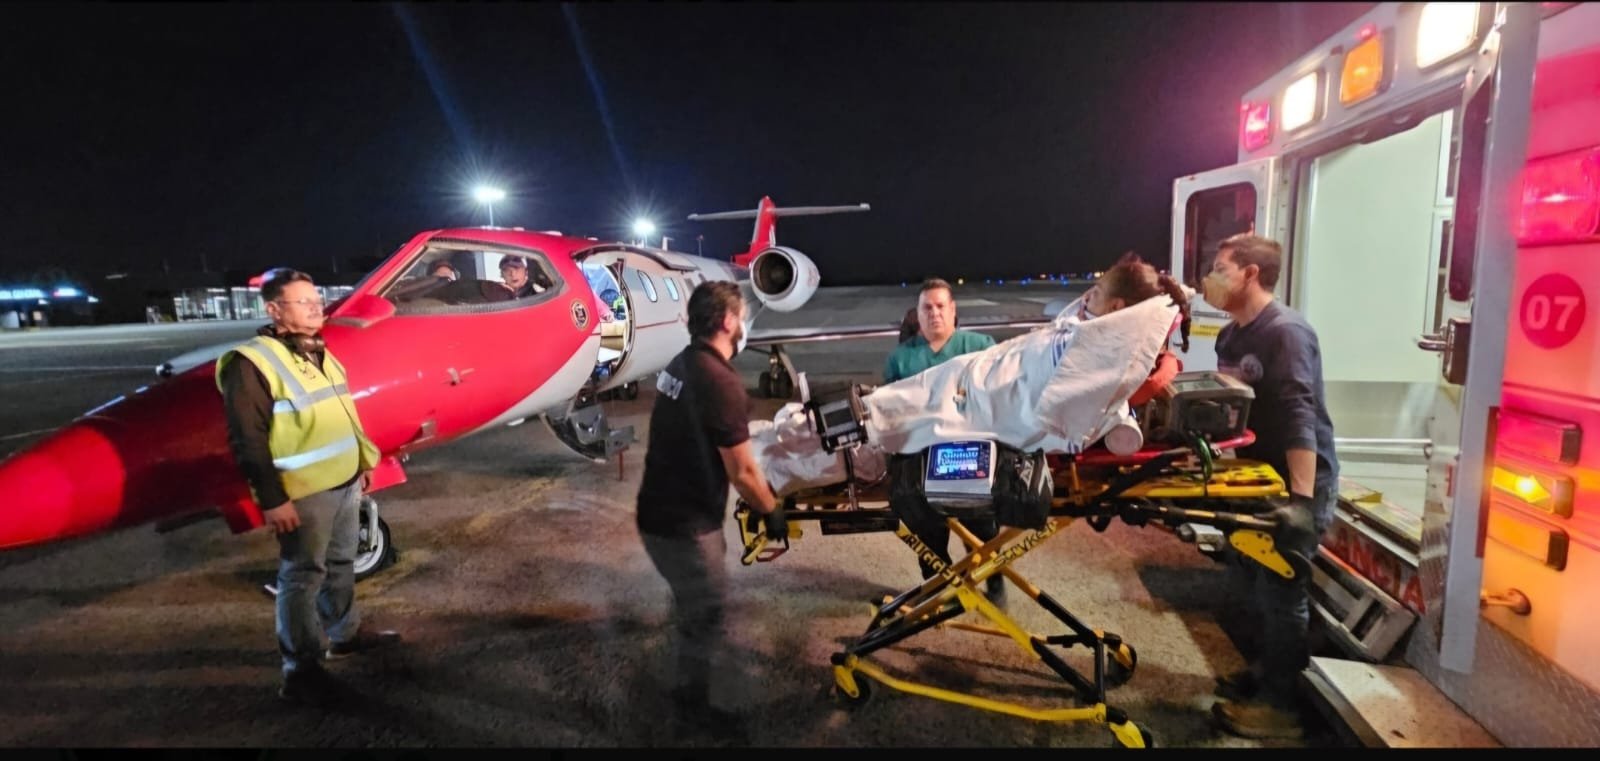
A common reason for medevac is interfacility transfer. A community hospital may stabilize a patient, then determine that they need services available at a specialty center, such as advanced trauma surgery, neurocritical care, transplant services, cardiac intervention, burn treatment, or ECMO capability.
These transfers can involve patients on mechanical ventilation, continuous IV medications, invasive monitoring, or other life-support measures. The transport team must be prepared to continue hospital-level care throughout the flight, not simply monitor the patient while in transit. Aircraft configuration and medical staffing should match the patient’s current condition and anticipated risks.
Patients injured or sick far from home
Travelers can become ill or injured anywhere: during a vacation, overseas work assignment, cruise, business trip, or visit with family. Local care may be appropriate initially, but the patient or family may need transfer to a hospital closer to home, existing specialists, insurance networks, or long-term support.
Medical repatriation is especially valuable when a patient cannot sit upright for a commercial flight, requires continuous oxygen or medication, has limited mobility, or needs a clinician during travel. Cross-border transfers also require careful coordination of airport access, medical records, ground ambulances, receiving-facility acceptance, and required travel documentation.
Newborns, children, and high-risk obstetric patients
Neonatal and pediatric patients require more than a smaller stretcher. They may need age-specific equipment, medication dosing, airway support, incubator capability, and a transport team trained to recognize rapid changes in young patients.
A premature or critically ill newborn may need transfer to a neonatal intensive care unit that can provide a higher level of support. Children with trauma, congenital heart conditions, severe respiratory illness, or complex neurological needs may also require pediatric air ambulance transport when the necessary specialty care is not available locally.
High-risk obstetric transport can be necessary when an expectant mother develops complications requiring maternal-fetal medicine, a higher-level labor and delivery unit, or urgent specialty intervention. In these cases, timing and clinical planning are essential because both maternal and fetal needs must be considered.
Patients who cannot safely fly commercially
Commercial airline travel is not automatically safe just because a patient is awake and communicating. Cabin altitude, prolonged sitting, limited space, connection delays, and lack of onboard clinical resources can make a standard flight unsuitable for certain conditions.
A patient may need a medical escort on a commercial flight if they are stable but require assistance, oxygen coordination, wheelchair transfers, medication oversight, or observation. A dedicated air ambulance may be more appropriate if the patient needs a stretcher, cardiac monitoring, suction, ventilator support, continuous infusion therapy, or the ability to respond immediately to a decline in condition.
The distinction matters. Sending a patient on a commercial flight when their needs exceed the available support can create avoidable risk. On the other hand, an air ambulance may not be necessary for a stable patient whose physician clears commercial travel with the right arrangements.
When is a medevac flight the safer option?
A medevac flight is considered when the patient needs more capability than a ground ambulance or commercial carrier can offer across the required distance. It may also be necessary when geography, traffic, terrain, border crossings, or weather make ground transport impractical.
Transport planning should answer four operational questions:
- Is the patient stable enough to move, and what care must continue during transport?
- How quickly must the patient reach the receiving hospital or home region?
- Can the destination accept the patient and provide the required specialty care on arrival?
- Which transport method offers the safest balance of speed, clinical capability, and cost?
Those questions are not administrative details. They determine whether the mission calls for a helicopter, a fixed-wing medical jet, a critical care team, a neonatal configuration, or a commercial medical escort.
Helicopter or medical jet?
Helicopters are often used for urgent regional transfers and scene responses where direct access and speed matter most. They can be valuable when a patient needs rapid movement from an accident scene or smaller hospital to a trauma center, particularly where road travel would cause a significant delay.
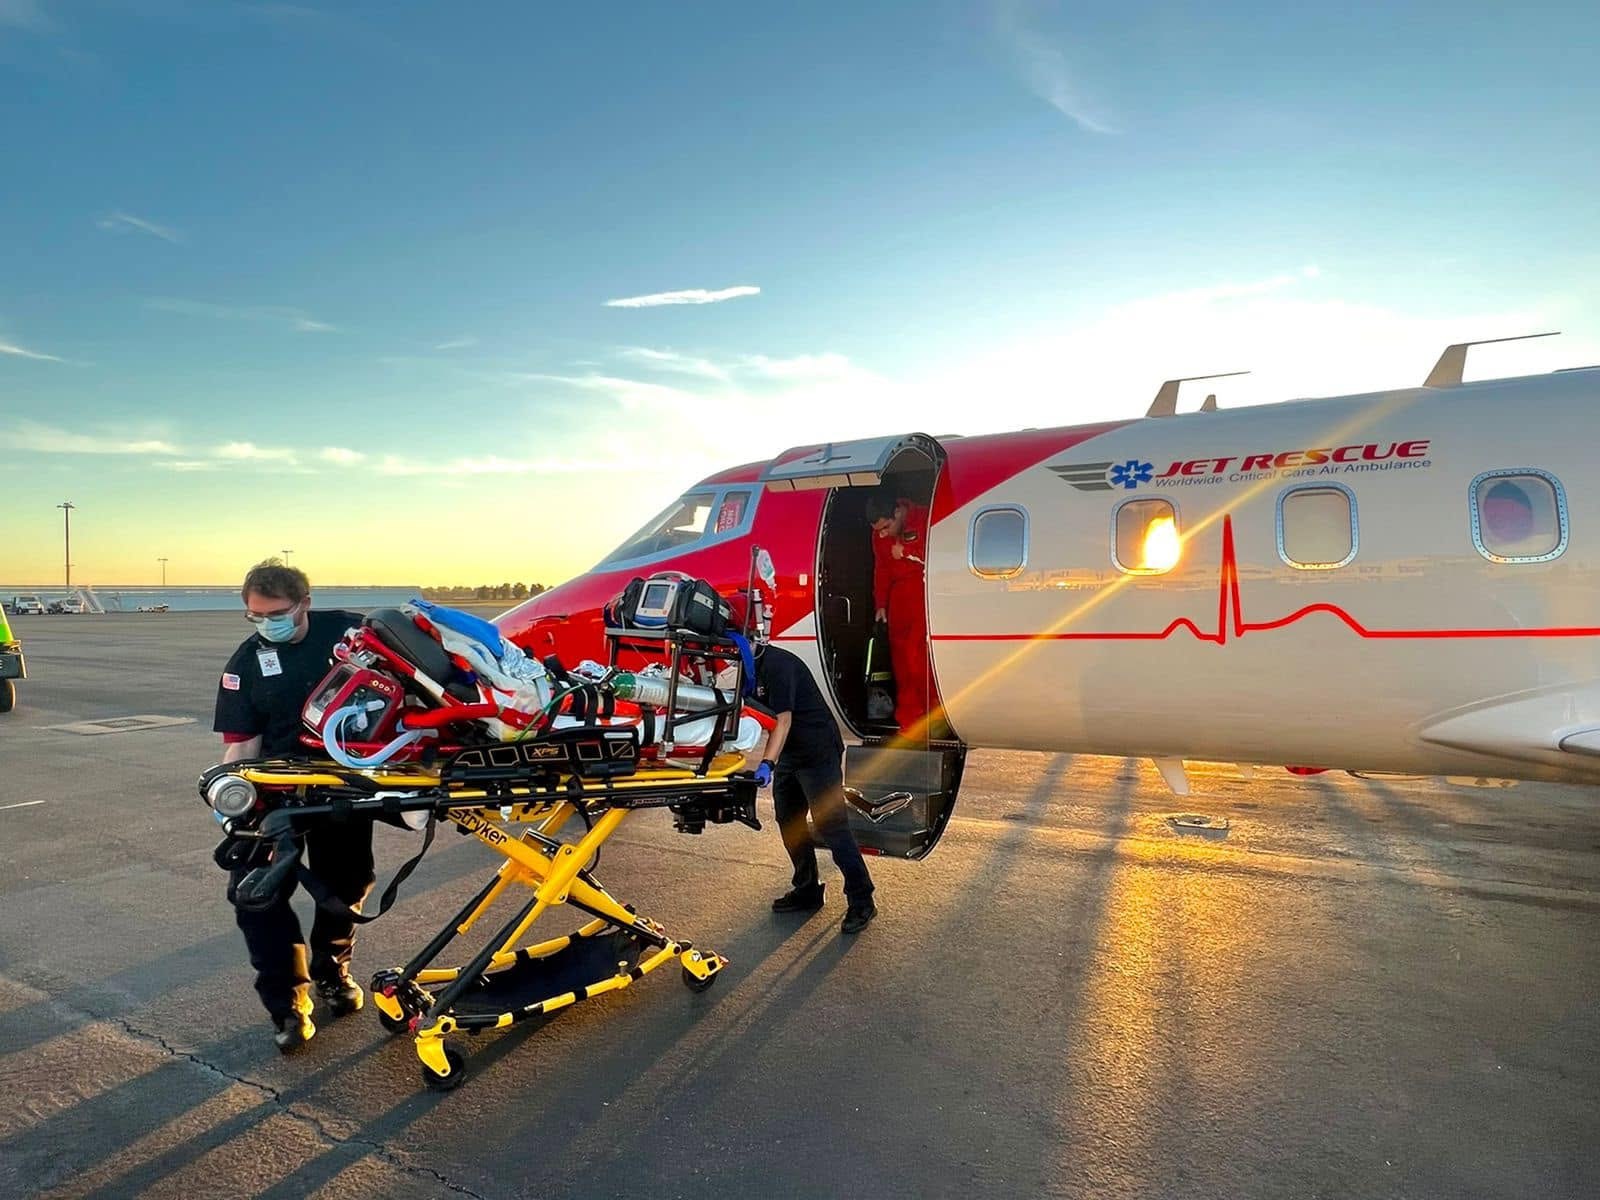
Fixed-wing air ambulances are generally used for longer domestic and international missions. They offer greater range, room for equipment and clinical personnel, and the ability to transport patients across states, countries, and continents. For a patient requiring intensive monitoring or advanced life support, the aircraft functions as a controlled clinical environment in the air.
The right option depends on more than mileage. Airport availability, runway requirements, weather, patient loading needs, and the level of onboard care all affect the decision.

Conditions that commonly require medical air transport
There is no single list that determines eligibility, but medevac is frequently arranged for trauma, stroke, heart conditions, respiratory failure, sepsis, neurological emergencies, severe burns, organ transplant needs, and complex post-surgical complications. It is also used for patients who are medically stable but cannot travel normally after hospitalization or injury.
The diagnosis alone does not decide the mission. A stroke patient may need urgent air transport if they are outside the reach of a stroke center. A patient recovering from surgery may need non-emergency medical transport if they are cleared to travel but need a stretcher and medical supervision. Someone with the same diagnosis may safely travel by ground or commercial flight depending on their vital signs, treatment plan, and destination.
For high-acuity cases, the referring team and transport medical director should review the patient’s records, current support requirements, weight and mobility considerations, infection-control needs, and likely in-flight risks before departure.
What families and case managers should do first
If a patient has a life-threatening emergency now, call 911 or local emergency services. Emergency responders can assess the situation and activate the appropriate local resources. Do not delay emergency care while trying to arrange a long-distance private transfer.
For a hospital-to-hospital or repatriation transfer, begin by confirming the treating physician’s assessment and identifying an accepting receiving facility. A qualified air medical provider can then coordinate the mission details, including bedside-to-bedside ground transportation, medical crew selection, aircraft configuration, records transfer, and international logistics when needed.
Have the patient’s diagnosis, current location, destination, treating physician contact, recent clinical notes, medication list, oxygen or ventilator requirements, and insurance information available. A quick, accurate clinical briefing helps the transport team determine the correct level of service without losing time.
Coverage and payment can vary. Some insurance plans, travel policies, employer programs, and government arrangements may cover medically necessary air transport, while other missions may require private payment. Verification should happen early, but urgent clinical decisions should remain based on safety and medical necessity.
Medevac is a clinical decision, not just a travel decision
The purpose of medevac is not simply to move someone faster. It is to preserve continuity of care when ordinary transportation cannot meet the patient’s medical or logistical needs. The safest mission is one built around the patient’s condition, with the right team, equipment, receiving plan, and route in place before takeoff.
For families and healthcare professionals under pressure, the clearest next step is to ask one direct question: can this patient get where they need to go without losing the level of care they need? If not, a specialized air medical team can help turn an urgent, complex transfer into a controlled clinical operation.
Tell us about the patient
A mission coordinator answers 24 hours a day. The benefits review is free and carries no obligation.